

A chiropractor should not assume that a painful rib is out of place or promise to push it back into position. Rib or chest pain needs assessment first; a suspected dislocation, fracture or medical cause requires medical evaluation rather than an adjustment.
- Can a chiropractor realign a rib out of place? Assessment must establish what is causing the symptoms first.
- Mychiro is a chiropractic clinic in Bondi Junction; its services are not a substitute for emergency chest-pain assessment.
- Tenderness, clicking or pain with movement does not establish that a rib is displaced.
- Call 000 for severe chest pain, breathing difficulty or other signs of a medical emergency.
Can a chiropractor realign a rib out of place?
A feeling that a rib is out of place is not a diagnosis of a displaced rib. The phrase describes how an area feels, but it does not establish which structure is involved or whether manipulation is appropriate.
Mychiro provides chiropractic services in Bondi Junction. Whether any chiropractic care is appropriate depends on assessment, relevant medical history and referral needs—not on the wording used to describe the pain.
An assessment should address the following questions before anyone proposes hands-on care:
- Check urgency. Does the history suggest a need for emergency or prompt medical assessment?
- Describe symptoms. Where is the discomfort, when did it begin, and what other symptoms accompany it?
- Consider causes. Is there a reasonable working explanation, and what still needs investigation?
- Discuss next steps. Is medical referral needed, or is a discussion of musculoskeletal care appropriate?
These steps are not a home diagnostic test. You cannot confirm a displaced rib by pressing on a tender spot or comparing both sides in a mirror.
Why this matters
The words rib out of place suggest a simple mechanical problem with a simple mechanical answer. That framing can distract from the more important question: why does your chest or upper back hurt?
Australian chest-pain guidance from Healthdirect distinguishes symptoms requiring emergency assistance from those needing other medical assessment. It does not recommend assuming that pain comes from a rib joint because movement reproduces it.
For a reader considering an appointment in 2026, the practical decision is therefore assessment before adjustment. A description of a technique is not evidence that the technique is appropriate for your symptoms.
When should rib or chest pain receive urgent medical attention?
Call 000 if you have severe chest pain, difficulty breathing, collapse, or chest discomfort accompanied by concerning symptoms such as sweating or feeling faint. Pain spreading to the arm, jaw or back also warrants urgent attention. Do not drive yourself if you suspect a medical emergency.
Healthdirect's Chest pain guidance is an Australian public-health reference for recognising these warning signs. If you are unsure whether symptoms are urgent, seek medical advice rather than testing whether stretching or pressure changes the pain.
Rib pain following an accident, fall or blow also needs appropriate medical assessment. New breathing difficulty, coughing up blood or worsening chest pain after an injury should not be managed as a routine chiropractic presentation.
For non-emergency health advice in Australia in 2026, Healthdirect's nurse service is available on 1800 022 222. Calling for advice is not a substitute for calling 000 when symptoms suggest an emergency.
What can “a rib out of place” actually mean?
People use this phrase for different sensations: a sharp spot beside the spine, discomfort around the chest wall, clicking, or pain during a deep breath. Those descriptions help explain the experience, but none identifies the cause on its own.
The distinction between a symptom description and a structural diagnosis matters. A confirmed dislocation means something different from tenderness or discomfort near a joint.
| Description or finding | What it establishes | What it does not establish |
|---|---|---|
| A tender spot near a rib | Pressure reproduces discomfort | That the rib has moved out of position |
| Pain with twisting or breathing | Those activities provoke symptoms | That the cause is exclusively muscular or joint-related |
| Clicking around the chest wall | A sound or sensation occurs | That a rib needs manipulation |
| A suspected fracture or dislocation | An injury needs medical assessment | That routine chiropractic adjustment is appropriate |
The RACGP's clinical discussion of Musculoskeletal chest wall pain explains why localisation and tenderness alone cannot rule out serious causes. Use that principle when interpreting symptoms, rather than trying to name a condition from an online checklist.
A clinician can explain a working diagnosis, its limits and any need for further investigation. You can ask for that explanation in plain language.
Does a true rib dislocation need a different approach?
A suspected true dislocation needs medical assessment, not an assumption that an adjustment will reposition it. The same applies when a fracture is suspected.
Do not ask a friend or family member to press, squeeze or twist your chest to relocate a rib. Avoid attempting a forceful self-adjustment while the cause remains uncertain.
NHS guidance on Broken or bruised ribs describes injury-related symptoms and circumstances requiring urgent help. It is relevant to understanding why pain after trauma needs an injury assessment rather than a promise of realignment.
The useful question is not whether a practitioner offers a rib technique. It is whether the diagnosis and proposed management are appropriate for the person being assessed.
Why the next step varies
The same phrase—rib out of place—can describe very different presentations. An appropriate next step depends on information that a search query cannot supply.
- How symptoms began: Pain after a fall or impact requires a different assessment from discomfort without an obvious injury.
- Associated symptoms: Breathlessness, fever, faintness or feeling generally unwell are important information for the assessing clinician.
- Symptom pattern: Persistent, worsening or changing pain needs reassessment rather than repeated assumptions about alignment.
- Medical history: Previous fractures, osteoporosis, heart or lung conditions, and other relevant diagnoses affect clinical decisions.
- Medicines: Tell the clinician about prescription medicines, including anticoagulants, before any discussion of hands-on care.
- Examination findings: The history and examination determine whether referral or further investigation needs consideration.
None of these factors confirms a diagnosis by itself. Bring the information together with a qualified health professional rather than using one reassuring detail to dismiss the rest.
What should happen before anyone proposes an adjustment?
You should have an opportunity to describe your concern and understand the proposed next step. An appointment does not commit you to manipulation.
A useful discussion follows this sequence:
- History: Explain the onset, location, progression and accompanying symptoms, including any injury.
- Assessment: Ask what the clinician is checking and whether medical evaluation is needed first.
- Explanation: Request a clear account of the working diagnosis and remaining uncertainty.
- Choices: Discuss the proposed approach, alternatives, relevant risks and the option not to proceed.
- Review: Agree on what changes require reassessment or medical attention.
Before consenting, you can ask whether hands-on care is necessary at that visit. You can also decline a technique or request time to consider the information.
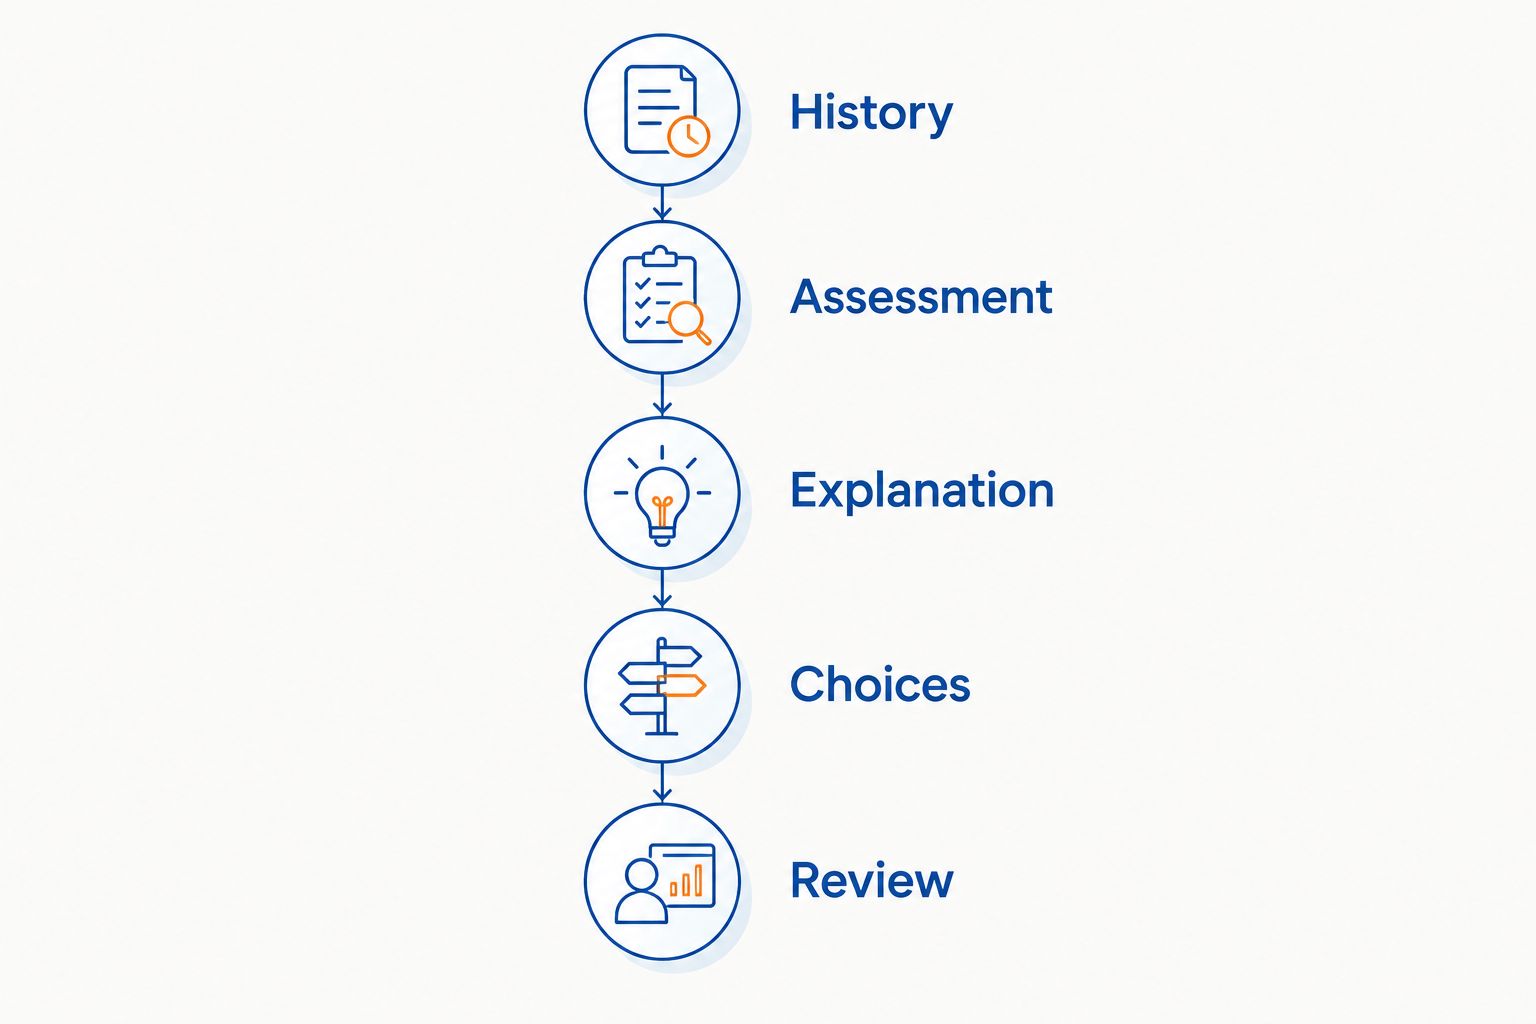
This decision sequence remains useful in 2026 regardless of the name given to a manual technique. A confident explanation of realignment should not replace discussion of uncertainty, risks or referral.
How do medical assessment and chiropractic assessment differ here?
Choose the assessment pathway according to your symptoms, not a preferred technique. Emergency symptoms belong with emergency services; unexplained chest symptoms or suspected injury require medical assessment.
The table below compares the purpose and limits of different pathways. It does not rank practitioners or recommend a service for an undiagnosed condition.
| Pathway | Appropriate purpose | Limitation to understand |
|---|---|---|
| Emergency services | Assess potentially urgent chest symptoms or serious injury | Not a routine pathway for ongoing non-urgent musculoskeletal questions |
| GP or other medical assessment | Investigate unexplained symptoms, assess injury and consider referrals | Further assessment or investigation can still be necessary |
| Chiropractic assessment | Discuss musculoskeletal concerns and whether chiropractic care is appropriate | Does not replace medical investigation of suspected chest disease, fracture or dislocation |
If you are uncertain about the distinction, start with medical advice. The related guide on when back pain needs a chiropractor versus a doctor discusses that decision more broadly; chest-pain warning signs still take priority.
Does a popping sound prove that a rib moved back?
A popping sound does not prove that a rib was displaced or has been repositioned. Sound alone is not a diagnosis or a measure of whether care was appropriate.
Ask the clinician what findings support the explanation being offered. Avoid judging a procedure by whether it produces a crack, a dramatic movement or an immediate change in sensation.
Do I need an X-ray before anyone touches the area?
The need for imaging depends on the clinical assessment, not simply on the phrase “rib out of place”. A qualified clinician should explain whether imaging is indicated and what question it would help answer.
Imaging is not something to demand solely to demonstrate alignment. Conversely, do not accept reassurance based only on a hands-on examination when the clinician identifies a reason for medical investigation.
How many appointments would a rib problem require?
There is no responsible appointment count for an undiagnosed rib complaint. The cause, assessment findings and agreed plan must come before a discussion of visit frequency.
For any proposed care plan in 2026, ask what will be reviewed and what would lead to a change in approach. Do not use a pre-set package or a promise of realignment as a substitute for an individual explanation.
What can you prepare before an assessment?
Write a short account of the symptoms rather than repeatedly testing the painful area. Include what you were doing when symptoms began and whether they have changed.
Useful information includes:
- The location of the discomfort and whether it spreads elsewhere.
- Any fall, impact, recent illness or persistent cough.
- Breathing symptoms, fever, dizziness or other accompanying changes.
- Relevant diagnoses, medicines and previous investigations.
- What you have already tried and whether symptoms changed afterwards.
Tell the clinician if you are worried about a particular procedure. You do not need to agree to an adjustment to ask questions about assessment or referral.
Avoid copying forceful rib-manipulation videos while waiting for advice. New or worsening symptoms should prompt reassessment, not a harder attempt to make the area click.
FAQ
Can a chiropractor realign a rib out of place?
A chiropractor should not promise to realign a rib without establishing what is causing the symptoms. A suspected dislocation, fracture or medical cause requires medical assessment rather than routine manipulation.
How do I know whether my rib is actually out of place?
You cannot confirm a displaced rib from tenderness, clicking or pain with movement alone. Describe the symptoms to a qualified health professional and seek medical assessment when injury or chest symptoms are involved.
Should I see a doctor or a chiropractor for rib pain?
Seek medical assessment for unexplained chest symptoms, suspected injury or uncertainty about the cause. Call 000 for severe chest pain, breathing difficulty, collapse or other emergency warning signs.
Can I push a rib back into place myself?
Do not attempt to push or force a painful rib into position. The sensation does not establish a dislocation, and forceful self-manipulation is not an appropriate diagnostic test.
Does pain when I take a deep breath mean a rib needs adjusting?
Pain with a deep breath does not establish that a rib needs adjusting. Seek medical advice, particularly if the pain is new, follows injury or occurs with breathing difficulty or illness.
Does a crack during an adjustment prove that a rib is back in place?
A crack does not prove that a rib has been repositioned. Ask what diagnosis and assessment findings support any explanation of the procedure.
What should I ask before agreeing to hands-on care?
Ask about the working diagnosis, uncertainty, proposed approach, alternatives and relevant risks. You can decline a technique or ask whether medical assessment should come first.
One last thing
Ask what “out of place” means before agreeing to a procedure intended to correct it. A useful answer distinguishes a description of discomfort from a confirmed structural injury and explains what remains uncertain.
Mychiro is a chiropractic clinic in Bondi Junction for people seeking chiropractic assessment; it is not an emergency chest-pain service. When reading health information in 2026, keep that boundary clear: the decision about care follows assessment, not an appealing explanation about alignment.
Related guides
- How to prepare for your first chiropractor appointment
- What to expect from spinal manipulation
- How chiropractors coordinate with GPs on imaging referrals



